
Endoscopic brow lift
Before / after
Real cases from the practice, unretouched, framed on the treated area only. Each result is individual and does not predict yours.
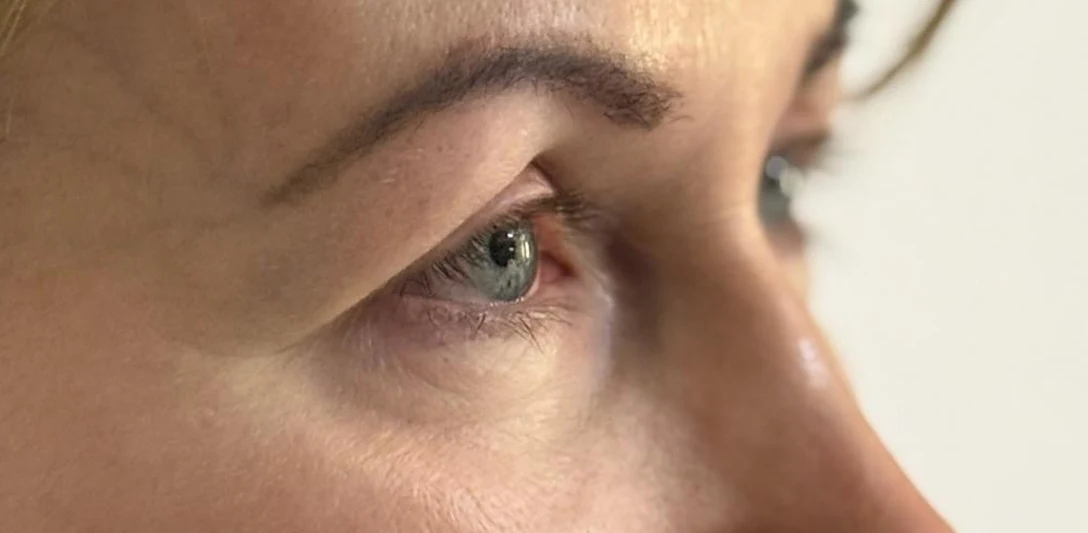
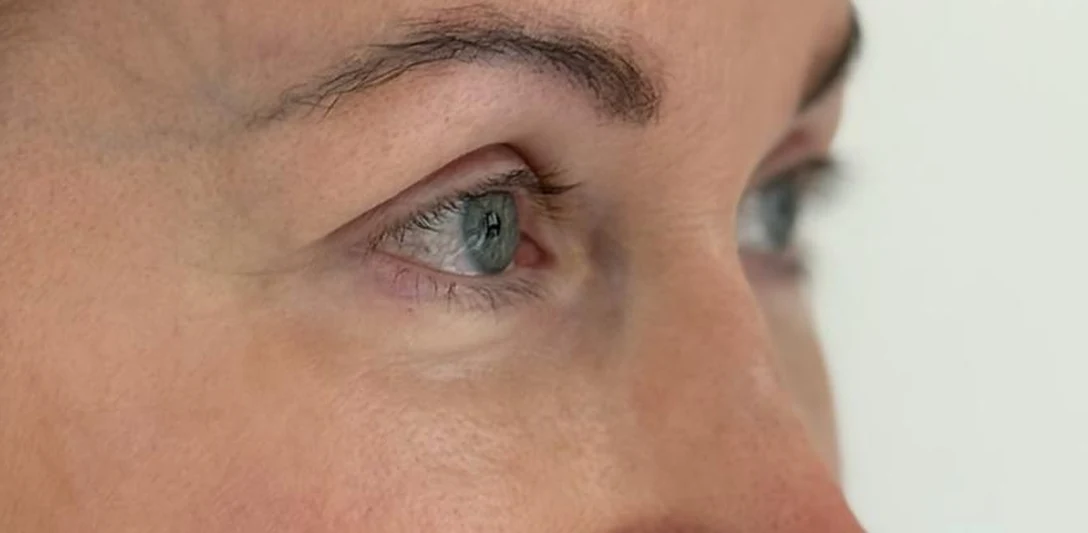
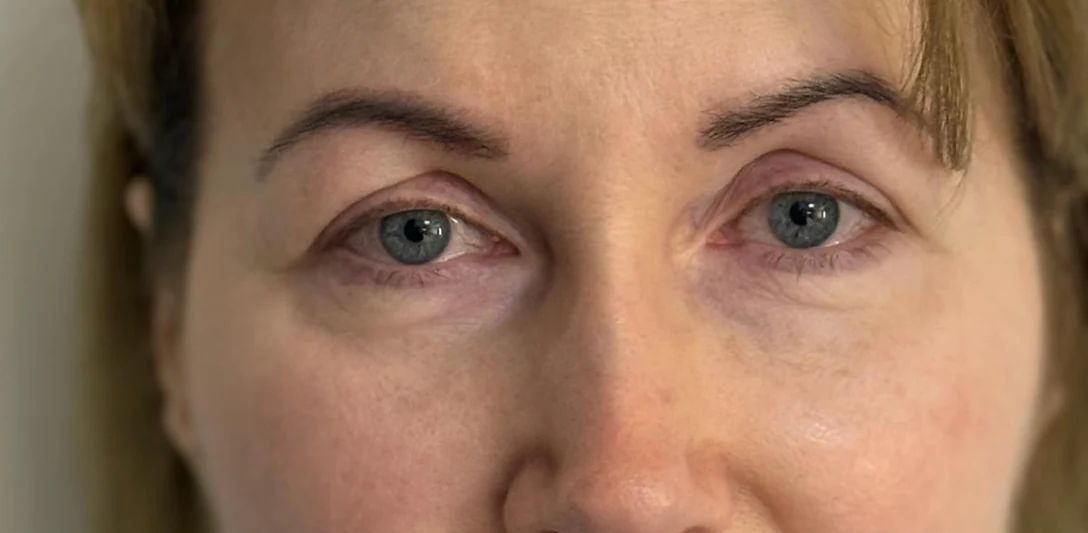
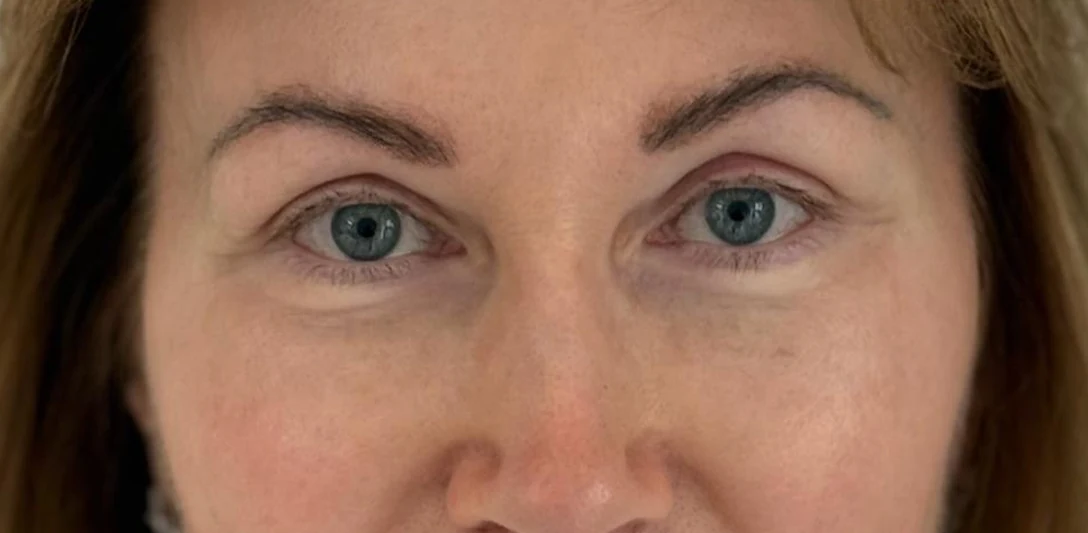
Photographs published with the patients’ written consent.
Written and reviewed by Dr Bernard Hayot, ophthalmologist, RPPS 10003926226.
Endoscopic brow lift
I prefer to speak of eyebrow repositioning rather than of a lift, since the latter term can suggest an excessively raised eyebrow and a frozen or surprised expression, far from the natural look we are seeking. The aim here is quite different: to return the eyebrow to the position it naturally held a few years ago, respecting the balance and the expression of the gaze.
This repositioning opens up the gaze by restoring harmony between the eyebrow and the upper eyelid. The procedure is performed endoscopically, through micro-incisions hidden in the scalp, so that any scarring is concealed, although its visibility depends on healing.
Using an endoscope and specific instruments, the forehead is gently dissected and the periorbital ligaments are released, relieving the tension weighing on the eyebrow area. Once the eyebrow has been repositioned with precision, the forehead is stabilised in its new position with micro-screws. This step ensures that the result lasts, while preserving a natural expression.
My experience with the endoscopic brow lift
I performed my first endoscopic brow lifts over 30 years ago, after training in the United States with Dr Nicanor Isse, one of the pioneers in this field. Back in Paris, I applied the technique I had learned, which was then considered innovative. I quickly identified two major limitations, however: results that did not last well over time, and a significant rate of eyebrow asymmetry after surgery.
Faced with these findings, I chose to set this approach aside for many years.
For the past two or three years, though, I have decided to bring the endoscopic brow lift back into my practice. Why? Because, as an oculoplastic surgeon, it now seems essential to me to know how to reposition the eyebrow in order to enhance the whole gaze. The eyebrow and the upper eyelid form an anatomical unit: treating one without the other often results in a lack of harmony and naturalness.
Current techniques are more precise and better controlled, and they make it possible to achieve results that are subtle, natural and long-lasting. It is this evolution, both personal and technical, that I wish to share in this chapter.
What is an endoscopic brow lift?
Indications
• Sagging of the lateral third of the eyebrow, giving a tired or sad appearance.
• Weakening of the forehead with marked horizontal wrinkles.
• Skin laxity of the upper face.
• Congenital or post-traumatic eyebrow asymmetry.
• An aesthetic request to open up the gaze, often combined with blepharoplasty.
It is particularly indicated in young to middle-aged patients whose skin is still elastic and who do not require a full cervicofacial lift.
Description of the procedure
Anaesthesia and preparation
• Type of anaesthesia: general anaesthesia, or deep sedation with local anaesthesia.
- Duration of the procedure: 1 hr 30 to 2 hrs.
- Hospital stay: day case or one night in hospital.
Surgical technique
The procedure is performed with an endoscope, a miniaturised camera introduced under the skin, which gives a precise view of the structures through small incisions hidden in the scalp (2 to 5 incisions of 1 to 2 cm each).
- Incisions in the scalp, in the temporal and frontal areas.
- Subperiosteal dissection, down to the bone, as far as the supraorbital ridges.
- Release of the attachments of the frontalis and orbicularis muscles, allowing proper mobilisation.
- Repositioning of the tissues and suspension of the eyebrows with deep anchor sutures or resorbable fixation devices.
- Closure of the incisions with resorbable or non-resorbable sutures.
Immediate post-operative course
• Duration of oedema and bruising: 7 to 15 days.
- Temporary numbness of the forehead and scalp.
- Moderate pain, well controlled with simple painkillers.
- Sutures removed between 7 and 10 days if non-resorbable.
- Return to social activities: 10 to 15 days.
- Return to sport: 4 weeks.
Expected results
Duration of effect: 5 to 10 years, depending on skin quality and lifestyle.

Possible complications
Early complications:
- Seroma: sometimes requiring drainage.
- Infection: rare, prevented by antibiotic prophylaxis.
- Persistent pain: generally temporary.
- Temporary hair loss around the incisions.
- Temporary asymmetry of the forehead or the eyebrows.
Specific complications:
- Nerve injury: involvement of the frontal nerve (the temporal branch of the facial nerve), which may cause temporary or long-lasting weakness of the frontalis muscle (rare).
- Sensory disturbance of the forehead or scalp (hypoaesthesia or paraesthesia), either transient or longer-lasting.
- An insufficient result or aesthetic dissatisfaction.
- Recurrence of eyebrow ptosis in the long term.
Fees
The cost of the procedure depends on the fees of the surgeon, the hospital staff and the anaesthetist.
Clinic fees and equipment costs must also be taken into account. A personalised, detailed quotation will be provided at the end of the initial consultation.
OUR EXCHANGES WITH WEB USERS
This page is for information. It does not replace a consultation: every situation is judged on examination.